Leave Your Message

2026 Best Medical Simulation VR Solutions for Training?

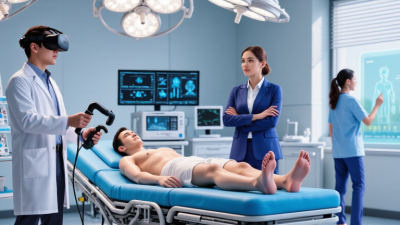
Medical Simulation Vr is reshaping how clinicians practice before entering high-pressure clinical environments. In a virtual emergency room, a trainee can assess a deteriorating patient, select equipment, and communicate with a team. The scenario can pause, restart, and record each decision. That repeatability matters.

Dr. Walter Greenleaf, a neuroscientist and medical technology researcher at Stanford University, has said, “Virtual reality is a powerful tool for changing human behavior.” His observation reflects the strongest value of Medical Simulation Vr: it can turn abstract protocols into visible, memorable actions. Learners may notice a falling oxygen level, hear an alarm, and practice calling for help without risking patient safety. They can also receive immediate performance data, including response time, missed steps, and communication gaps.

Still, excitement should not replace evidence. A headset cannot reproduce every physical sensation, emotional pressure, or unpredictable patient response. Some platforms offer convincing visuals but limited haptic feedback. Others collect detailed learner data without explaining how educators should interpret it. That is a real weakness. It deserves scrutiny.

The best solutions should support measurable learning objectives, realistic clinical workflows, instructor oversight, and secure data handling. They should fit existing curricula, not operate as isolated technology demonstrations. This guide examines leading Medical Simulation Vr solutions for 2026 through those practical standards. It considers clinical realism, usability, content quality, assessment tools, hardware comfort, scalability, and total cost. The goal is not to identify the most impressive headset. It is to identify systems that help people practice better, reflect honestly, and perform more reliably when real patients need them.

2026 Best Medical Simulation VR Solutions for Training?

What Medical Simulation VR Solutions Are

Medical simulation VR solutions are digital training systems that recreate clinical environments through headsets, interactive software, sensors, and sometimes haptic tools. They let learners examine a virtual patient, select equipment, perform procedures, and respond to changing vital signs. A useful system also records timing, errors, communication, and clinical decisions for instructor review.

The need is practical. The World Health Organization’s Global Patient Safety Report 2024 estimates that one in ten patients experiences harm during healthcare, with more than half considered preventable. VR cannot replace supervised practice, real equipment, or human judgment. It can provide repeatable rehearsal before learners enter high-pressure settings. PwC’s 2020 VR training study found that learners completed training up to four times faster and reported higher confidence than classroom learners. That evidence is encouraging, but it was not limited to medical education.

A strong medical simulation platform should support realistic scenarios, adjustable difficulty, multilingual guidance, performance analytics, and structured debriefing. It should also protect learner data and connect with existing education systems. Haptic feedback can improve procedural realism, though the sensation may still feel artificial. That limitation matters. A learner who succeeds in a headset may struggle with patient anxiety, tissue resistance, or team communication. Instructors should compare virtual performance with observed clinical skills, not accept automated scores without question. The most credible solutions use validated scenarios, transparent assessment criteria, and repeated review by qualified healthcare educators.

2026 Best Medical Simulation VR Solutions for Training

What medical simulation VR solutions are commonly evaluated for: clinical realism, learner interaction, assessment, scalability, and operational efficiency.

Index scale: 1 = limited capability, 5 = strong capability. The scores represent a comparative planning framework for common medical simulation VR solution requirements, not company-specific performance data.

Core Technologies Behind Medical Training in VR

2026 Best Medical Simulation VR Solutions for Training?

Core Technologies Behind Medical Training in VR

Medical training in VR now depends on more than realistic graphics. High-resolution headsets, six-degree-of-freedom tracking, and low-latency rendering create a convincing clinical workspace. Trainees can inspect a virtual airway, adjust an oxygen mask, and respond to changing vital signs. Spatial audio adds practical pressure. A monitor alarm behind the learner may demand immediate attention.

Haptic controllers provide resistance during needle placement, palpation, and instrument handling. However, virtual pressure still feels different from living tissue. That limitation matters. Reliable programs combine haptics with supervised practice on physical models. Motion capture can record hand position, posture, and procedure timing. Integrated physiological sensors may also measure stress, though readings can be inconsistent.

Artificial intelligence can alter scenarios according to learner performance. A patient may deteriorate after delayed treatment, while an experienced learner faces more complex complications. Yet adaptive systems require careful clinical review. Poor training data can reinforce unsafe recommendations. Secure data storage, role-based access, and clear consent procedures are equally important. Instructors should inspect performance dashboards rather than trust automated scores blindly. The technology is useful, but not infallible.

Key Training Applications Across Medical Specialties

Medical simulation VR is moving beyond novelty. The strongest solutions support specialty-specific practice, measurable feedback, and repeatable assessment.

In emergency medicine

In emergency medicine, trainees can manage airway obstruction inside a crowded ambulance bay. They can select equipment, adjust oxygen flow, and respond to falling oxygen saturation. Obstetric modules can recreate postpartum hemorrhage, including blood-loss estimates and urgent team communication. In surgery, realistic tissue resistance and instrument tracking help learners rehearse laparoscopic movements. Radiology scenarios can place subtle findings inside noisy clinical images. These details matter because pressure changes decision-making.

The World Health Organization reports that approximately one in ten patients experiences harm in healthcare, with more than half considered preventable.

VR cannot remove every clinical risk, but it can expose weak decisions before patient contact. The AAMC’s 2024 physician workforce report projects a possible U.S. physician shortage of up to 86,000 by 2036. Scalable practice may help, especially for rural hospitals and rotating teams.

The evidence is promising, not perfect.

The evidence is promising, not perfect. Haptic feedback can feel artificial, and headset discomfort may limit long sessions. Some simulations also reward fast clicks rather than thoughtful care.

Training leaders should compare completion times, clinical accuracy, communication quality, and retention after several weeks. A good platform also provides instructor controls, accessible design, secure learner data, and exportable assessment records.

Without these safeguards, impressive graphics become expensive theatre.

How to Evaluate VR Solutions for Healthcare Education

2026 Best Medical Simulation VR Solutions for Training?

Evaluating VR for healthcare education starts with the learning objective, not the headset. Can the system improve airway assessment, surgical planning, or emergency communication? Clinical educators should map each module to measurable competencies and existing assessment methods. A visually impressive scenario may still teach very little.

Test the basics. Check visual clarity, hand tracking, audio quality, and response time during fast procedures. Latency matters. Learners notice. Ask whether students can repeat a case without excessive faculty support. Review accessibility features for limited mobility, visual differences, and motion sensitivity. Hygiene also matters. Shared headsets need practical cleaning procedures between sessions.

Reliable evaluation requires evidence beyond a sales demonstration. Request validation studies, implementation data, and clear information about data storage. Confirm whether performance records can connect with the institution’s learning platform. Faculty should inspect scoring rules, because automated feedback can miss clinical nuance. A short pilot with nurses, physicians, and simulation technicians can reveal workflow problems early. It may expose uncomfortable weaknesses. That is useful.

Cost calculations should include training time, technical support, replacement equipment, and content updates. Measure completion rates, skill retention, learner confidence, and observed clinical performance. Do not treat confidence as competence. No scorecard is perfect. Educators should document what the system measures well and where human assessment remains necessary.

Leading Features and Trends Shaping Medical VR in 2026

Medical simulation VR in 2026 is moving beyond impressive visuals. The strongest systems model clinical decisions, not only procedures. In training sessions, learners may assess a deteriorating patient, choose an intervention, and explain their reasoning. That sequence matters. Haptic controllers can represent resistance during needle placement or chest compression. Yet sensation remains limited. Developers are improving hand tracking, eye tracking, and spatial audio to make practice more responsive.

Adaptive scenarios are becoming a leading feature. The virtual patient can change breathing, speech, or vital signs after each decision. This creates pressure without placing a real patient at risk. Artificial intelligence can provide immediate feedback on timing, communication, and missed safety checks. Expert review remains essential, because automated scoring may reward a technically correct but clinically poor choice. Training data should be traceable, protected, and separated from unnecessary personal information.

Interoperability will shape adoption. VR records should connect with learning platforms and competency frameworks through clear, secure standards. Wireless headsets, lighter hardware, and offline access can support busy hospitals and rural programs. Accessibility also needs attention, including seated modes, captions, adjustable controls, and motion-sickness settings. A weakness is easy to overlook: realistic simulation can still teach unrealistic habits. Clinical educators must test scenarios against current protocols and local workflows. Some lessons will need revision. That is a useful failure, not a minor detail.

2026 Best Medical Simulation VR Solutions for Training? — Leading Features and Trends Shaping Medical VR in 2026
Medical VR Solution Type Primary Training Use Leading Features in 2026 Clinical Skills Developed Assessment and Data Capabilities Hardware and Deployment Needs Evidence and Maturity Key 2026 Trend
Immersive Surgical Procedure Simulation Preparation for common and complex surgical workflows before supervised operating-room practice. Anatomical visualization Step-by-step scenarios Branching complications Repeatable practice Instrument handling, procedural sequencing, anatomy recognition, decision-making and operating-room orientation. Tracks task completion, sequence errors, time-on-task, instrument selection and responses to intraoperative events. Standalone or tethered headsets, tracked controllers and optional haptic instruments; suitable for skills laboratories and simulation centers. Established training category; effectiveness is strongest when simulation is paired with faculty feedback and clinical practice. More adaptive scenarios that change difficulty according to learner performance rather than presenting identical cases to every trainee.
Emergency and Trauma Response VR Training for time-critical assessment, stabilization and coordinated emergency response. Dynamic patient deterioration Team scenarios Time pressure Crisis branching Primary survey, triage, prioritization, communication, resuscitation workflow and escalation decisions. Measures response time, intervention order, protocol adherence, communication events and missed critical actions. Wireless headsets with spatial audio; can be used individually or with multi-user networking for interprofessional teams. Established for scenario-based rehearsal; clinical transfer depends on alignment with local protocols and instructor debriefing. Integration of team-performance analytics and standardized after-action reviews for emergency medicine education.
Patient Examination and Diagnostic Reasoning VR Practice of history-taking, physical examination and differential diagnosis in standardized virtual patients. Conversational AI Virtual patient cases Multimodal findings Case variation Clinical interviewing, examination technique, information gathering, diagnostic reasoning and patient communication. Records questions asked, examination steps, selected tests, diagnostic hypotheses and justification of decisions. Headset, desktop or mixed-reality delivery; voice input and accessibility features improve hands-free interaction. Rapidly developing; automated feedback should be reviewed by educators, especially for nuanced communication and diagnosis. Generative conversational agents are being used to create more varied patient interactions while retaining educator-defined learning objectives.
Anatomy and 3D Medical Imaging VR Learning anatomy, pathology, spatial relationships and image-guided clinical planning. 3D anatomical models Layer isolation Image overlays Collaborative viewing Spatial understanding, anatomical identification, interpretation of imaging data and procedure planning. Assesses structure identification, labeling accuracy, spatial navigation and completion of guided learning activities. Standalone headsets or high-resolution workstations; medical image integration requires privacy controls and compatible data workflows. Well-established educational application; visual fidelity and curriculum integration are more important than immersion alone. Greater use of patient-specific, de-identified imaging and mixed-reality visualization for anatomy teaching and planning discussions.
Nursing and Bedside Care Simulation Rehearsal of routine and high-risk bedside procedures in controlled virtual environments. Medication scenarios Patient monitoring Infection control Care prioritization Patient assessment, medication safety, clinical observation, documentation, infection prevention and escalation of concerns. Captures vital-sign interpretation, medication checks, procedural sequence, documentation quality and escalation timing. Wireless headsets and hand tracking can reduce setup time; physical task trainers remain important for tactile procedures. Established as a supplementary method; it does not replace supervised practice with real equipment and patients. Blended curricula combining VR decision-making with physical task trainers for skills that require touch, force and dexterity.
Interprofessional Team Training VR Practice of collaboration among physicians, nurses, technicians, therapists and other healthcare professionals. Multi-user environments Role-based scenarios Voice communication Team debriefing Leadership, closed-loop communication, role clarity, handoffs, conflict management and shared situational awareness. Evaluates communication patterns, information sharing, leadership behaviors, response coordination and team workload indicators. Networked headsets, reliable connectivity and facilitator dashboards; requires clear role assignment and privacy-aware data handling. Growing adoption; technical latency and consistent audio are important for realistic team interaction. Expansion from individual skill scoring toward team-level analytics and competency-based interprofessional assessment.
Mental Health and Behavioral Health VR Training for therapeutic communication, de-escalation and assessment of behavioral health presentations. Emotionally responsive avatars Conversation branching De-escalation practice Safe repetition Empathy, active listening, risk assessment, trauma-informed communication and management of challenging interactions. Analyzes dialogue choices, tone-related inputs where supported, escalation triggers, safety actions and reflective responses. Headsets with spatial audio and voice interaction; careful content review is needed to avoid stereotyping or distressing representations. Developing evidence base; scenarios should be supervised and aligned with established communication frameworks. More focus on psychologically safe practice, learner consent, content warnings and culturally responsive virtual patients.
Rehabilitation and Physical Therapy VR Training for assessment, exercise instruction, motor rehabilitation and patient engagement. Motion tracking Interactive exercises Progress visualization Adaptive difficulty Movement assessment, exercise coaching, patient motivation, functional goal setting and safe progression of activities. Uses range-of-motion estimates, repetition counts, movement quality indicators and adherence records when supported by sensors. Headsets, motion controllers or external tracking; calibration and physical-space safety checks are essential. Established in selected rehabilitation applications; sensor accuracy and clinical oversight remain important. Combination of VR with motion sensing and remote monitoring to support personalized rehabilitation education and follow-up.
Mixed-Reality Procedural Skills Training Learning procedures while seeing physical instruments, equipment or task trainers alongside digital guidance. Real-world overlays Spatial anchoring Hands-free guidance Physical-digital integration Equipment setup, procedural precision, hand positioning, workflow sequencing and safe interaction with clinical devices. Can combine digital task completion data with sensor-based measurements from physical equipment or mannequins. Mixed-reality headsets, tracked environments and compatible physical trainers; setup and calibration are more demanding than fully virtual training. Emerging and expanding; strongest value is expected where tactile and spatial context are essential. Shift from fully virtual scenes toward hybrid learning that preserves physical sensation while adding real-time digital instruction.
Remote and Distributed VR Simulation Delivery of standardized training to learners across campuses, hospitals or geographic regions. Cloud management Remote facilitation Synchronized cohorts Central reporting Supports procedural rehearsal, communication, triage and team coordination when learners cannot access a shared simulation center. Central dashboards can compare completion, performance trends, participation and remediation needs across learner groups. Managed headsets, secure user authentication, stable network access and technical support; offline capabilities can improve resilience. Operationally mature in suitable settings; institutional IT, privacy and device-management policies are required. Growth of scalable simulation libraries and hybrid programs that combine local facilitation with centrally managed content.
AI-Assisted Adaptive Simulation Personalized practice that adjusts cases, feedback and difficulty to the learner’s performance. Adaptive pathways Automated hints Natural-language feedback Learning analytics Clinical reasoning, prioritization, error recognition, self-reflection and targeted remediation. Combines event logs, speech or interaction data, rubric-based scoring and longitudinal progress tracking. Requires headset or compatible computer, secure data architecture, validated scoring rubrics and educator oversight. Emerging capability; automated recommendations must be transparent, monitored and checked for bias or unsafe feedback. Human-in-the-loop assessment, explainable feedback and tighter integration with learning-management and competency-record systems.
Note: Medical VR is best used as a supplement to supervised clinical education. Physical examination, tactile procedures, patient safety practice and professional judgment still require appropriate real-world training and assessment.